An Anion Gap Calculator is a helpful tool for making sense of blood test results, especially when clinicians are checking for an acid-base imbalance or an electrolyte imbalance. To understand what the calculator is actually showing, it helps to know the difference between measured anions and unmeasured anions. That difference is the core of the anion gap, a calculated value that offers an valuable diagnostic clue in the right medical context.
At a basic level, an anion is a negatively charged particle. Blood chemistry depends on a delicate balance between positive charge and negative charge, and that balance is described by the principle of electroneutrality. While the body contains many charged substances, only some are routinely reported on a standard lab test. Others are present in serum but are not directly included in the usual electrolyte measurements. Recognizing this distinction makes it easier to interpret lab values and identify an underlying cause of abnormal results.
What are anions in laboratory blood analysis?
In blood chemistry, an negatively charged ion is any molecule or ion with a negative electrical charge. These elements help determine the overall serum concentration of charged particles in the body. Because the blood has to stay electrically neutral, the total amount of positive charge roughly matches the total amount of negative charge, even though individual substances may increase or decrease.
Anions are part of the broader group of electrolytic molecules, which includes both negatively charged and positively charged ions. In a typical clinical chemistry setting, clinicians focus on a small set of these ions because they are central to fluid balance, kidney function, and acid-base regulation. The remainder are present in serum but are not routinely measured on standard testing.
Many important anions in medicine are tied to the body’s metabolic state. Some are involved in transport, some are anions attached to proteins, and others are organic acids that can increase during illness. This is why a blood test result can be more than just a number: it can point toward a metabolic disturbance or a change in renal function. This gap helps summarize part of that chemistry by comparing what is measured against what is not.
What are reported anions?
Reported anions are the negatively charged substances routinely shown on a routine laboratory test or electrolyte screen. The main substances are chloride and bicarbonate. Although sodium is not an anion, it is often included in the assessment because it is the major measured cation and provides the positive side of the balance.
On a typical test, sodium, chloride, and bicarbonate are the most important lab values used to calculate the anion gap. Each is essential in a different way. Sodium represents the major extracellular cation, chloride helps preserve charge balance, and bicarbonate acts as a major buffer in acid-base regulation. Together, these measurements offer a snapshot of the body’s electrolyte pattern and help clinicians assess acid-base balance.
These measured values are part of the standard serum electrolytes obtained in many clinical settings. Their importance lies not only in the numbers themselves, but also in how they relate to one another. For example, a drop in bicarbonate with a corresponding rise in chloride may suggest a non-gap metabolic disturbance, while a drop in bicarbonate with an increase in unmeasured anions can point to a high anion gap process.
In other words, measured anions are the visible portion of the chemical picture. They are the substances a lab test directly reports, and they form the foundation for the Anion Gap Calculator’s calculated value.
What are unseen anions?
Unmeasured anions are negative-charge substances found in serum that are not routinely included in the usual electrolyte panel. They are still part of the body’s electrical balance, but they do not appear directly in the basic blood chemistry numbers used in the anion gap calculation. Typical examples include albumin, phosphate, sulfate, and lactate.
Albumin is especially important because it is one of the most abundant negatively charged proteins in blood. Even though it is not always thought of as a classic electrolyte, it greatly influences the charge balance. Phosphate and sulfate also contribute to the pool of unmeasured ions. Lactate becomes especially relevant when tissues are under stress or oxygen delivery is impaired, since elevated lactate can be a significant contributor to metabolic acidosis.
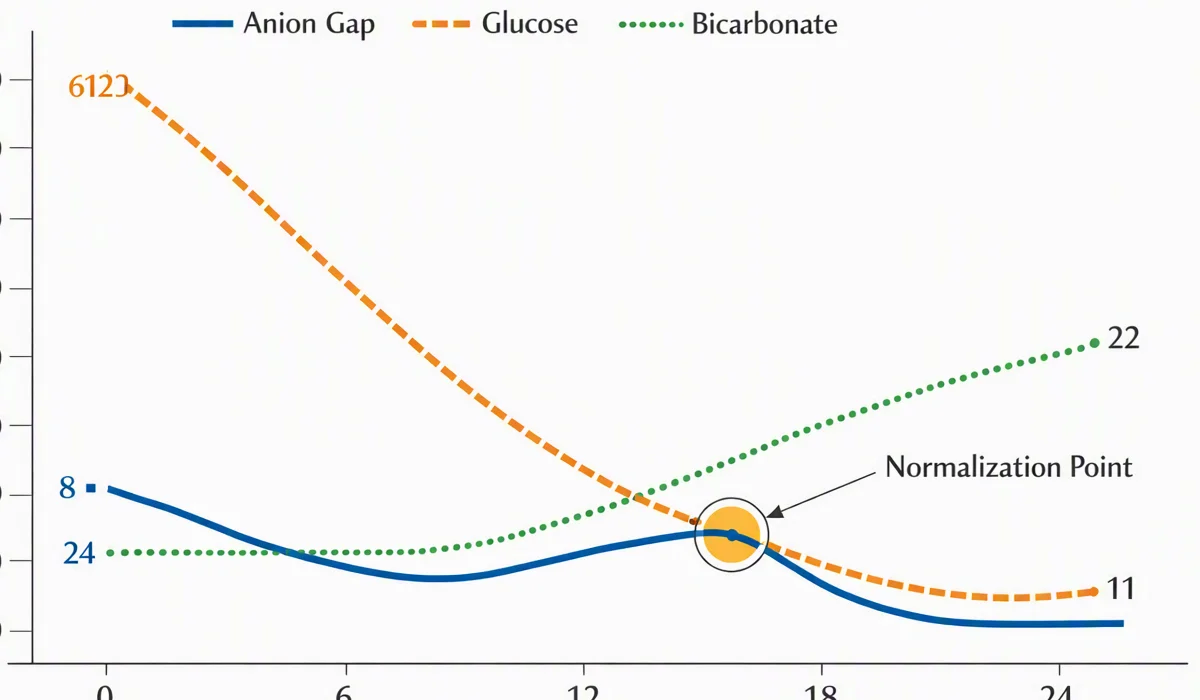
Other unmeasured anions include ketones, which can rise during fat metabolism when glucose cannot be used normally. These substances matter because they can accumulate without being directly reflected in the routine lab report. That is why the anion gap serves as a helpful estimate of the gap between what is measured and what is chemically present in the serum.
In practice, unmeasured anions often provide the real clue to the underlying cause of an abnormal result. They are a key part of the medical context, especially when the blood test shows signs of acid-base disturbance but the routine electrolyte numbers do not fully explain why.
How the anion gap is computed
The anion gap is a formula-driven estimate that compares the main measured cations and anions to infer the amount of unmeasured charge in the blood. The most commonly used formula is:
Anion gap = sodium − (chloride + bicarbonate)
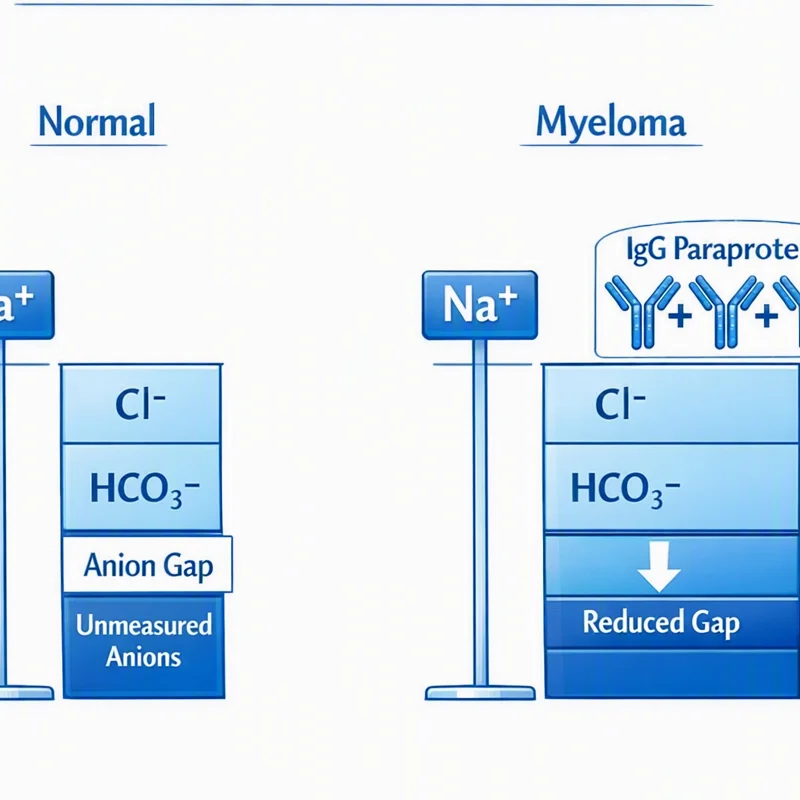
This formula works because of electroneutrality. Blood must preserve nearly equal total positive and negative charge, so if the measured ions do not fully account for the expected balance, the difference is assigned to unmeasured anions. In this way, the gap is not really a “gap” in the chemistry; it is a calculated estimate of what is missing from the basic serum electrolytes.
An Anion Gap Calculator uses this formula quickly and consistently. Clinicians use it to interpret serum electrolytes in context rather than in isolation. The result can help spot acid-base problems, follow changes over time, and support further evaluation when lab values are abnormal.
Because the anion gap depends on measured numbers, the result is only as accurate as the input data. Small shifts in sodium, chloride, or bicarbonate can affect the calculation. That is why the interpretation guide matters: a single result should be viewed alongside symptoms, history, renal function, and other lab findings rather than treated as a standalone diagnosis.
What is a high anion gap mean?
A high anion gap typically indicates there are increased unmeasured anions in the blood. This pattern is commonly associated with metabolic acidosis, a metabolic imbalance in which the body has retained acid or depleted bicarbonate in a way that is not completely balanced by chloride. The elevated gap is a diagnostic clue that encourages clinicians to identify the underlying cause.
One common cause is ketoacidosis. When the body metabolizes fat for energy, ketones accumulate and act as unmeasured acids. Another important cause is lactic acidosis, where lactate rises because of reduced oxygen supply, severe illness, or impaired metabolism. Both conditions can lead to significant shifts in blood test results and demand prompt medical attention.
Toxic alcohols are another classic cause of a high anion gap. Certain ingestions can result in the generation of acid metabolites that increase the burden of unmeasured anions. In these cases, the gap can be an initial warning sign before the full clinical picture becomes obvious.
Other causes may involve kidney dysfunction, shock, or severe metabolic disturbance. In every case, the high gap shows a change in the balance between measured and unmeasured components. It is not the diagnosis itself, but it can point strongly toward the diagnosis when interpreted correctly.
What does a standard or low anion gap mean?
A typical anion gap does not automatically mean everything is fine, and a reduced anion gap can also be meaningful. Sometimes, the result is explained by hypoalbuminemia, which means a low albumin level. Since albumin is a major unmeasured anion, lowered albumin lowers the expected gap and can make an otherwise concerning process look less apparent.
A reduced or unexpectedly normal result can also be caused by laboratory error. Because the anion gap is derived from other values, even small measurement issues in sodium, chloride, or bicarbonate can affect the final number. This is why doing again the test or looking over the full electrolyte panel is often an essential step if the result does not match the clinical picture.
Hyperchloremia can also reduce the gap. If chloride rises, the formula may produce a smaller calculated value even when other aspects of acid-base balance are abnormal. Similarly, paraproteinemia can create a low anion gap because abnormal proteins may alter electrical balance and change the expected balance of measured and unmeasured ions.
In short, a typical or decreased result should be read closely. It may reflect a genuine physiologic pattern, a change in albumin, an issue with the lab test, or an effect of another medical condition. The number alone is not adequate; interpretation depends on the broader medical context.
How to understand findings from an Anion Gap Calculator
Relying on an Anion Gap Calculator is easiest when you think of it as an reference guide rather than a diagnostic tool. The calculator applies the main serum electrolytes, follows the formula, and produces a result that can be compared with the expected reference range. That comparison helps reveal whether the gap is normal, elevated, or low.
After that, the result should be considered alongside the broader electrolyte panel, symptoms, and clinical history. If the gap is high, the next question is usually what unmeasured anion is responsible. If the gap is low or normal but there is still concern for illness, the question becomes whether albumin is low, whether there is hyperchloremia, or whether another factor is masking the abnormality.
Clinical interpretation also depends on acid-base balance. The anion gap is especially helpful when there is concern for acidosis or another metabolic disturbance. It does not replace a full evaluation, but it can refine the possibilities and guide the workup. In that sense, it is a bridge between raw lab values and clinical significance.
When interpreting results, it is also useful to ask:
- Are the serum electrolytes internally consistent? Is albumin low enough to affect the calculation? Do the symptoms match a high or normal gap pattern? Is there a likely underlying cause such as lactic acidosis, ketoacidosis, or toxic alcohol exposure? Could the result reflect laboratory error or paraproteinemia?
These questions help turn a calculated value into a useful clinical clue. The calculator is not the final answer, but it can sharpen thinking and support timely medical evaluation.
Typical questions about measured and unmeasured anions
The difference between measured and unmeasured anions is central to understanding the anion gap, but it also raises practical questions. The FAQ below addresses the most common ones and connects them to diagnosis, symptoms, and medical evaluation.
What is the distinction between detected and not directly measured anions?
Reported anions are the negative-charge substances directly reported on routine blood tests, particularly chloride and bicarbonate. Unmeasured anions are negatively charged substances present in serum that are not included in the standard electrolyte panel, such as albumin, phosphate, sulfate, lactate, and ketones. The discrepancy between them is what the anion gap helps estimate.
Which anions are typically measured on a standard electrolyte panel?
A standard electrolyte panel typically includes sodium, chloride, and bicarbonate. Sodium is the primary measured cation used in the anion gap formula, while chloride and bicarbonate are the primary measured anions. These lab values provide the basis of the calculation and provide essential information about acid-base balance and electrolyte imbalance.
Why does albumin affect the anion gap?
Albumin affects the anion gap because it is a important unmeasured anion in blood. When albumin is low, as in hypoalbuminemia, the anion gap may look lower than expected. This can mask an underlying acid-base disorder, so albumin correction is often important for precise clinical interpretation.
What conditions cause a high anion gap?
A high anion gap is commonly caused by metabolic acidosis with accumulation of unmeasured acids. Major causes include lactic acidosis, ketoacidosis, toxic alcohols, kidney-related metabolic disturbance, and other conditions that increase organic acids or ketones. The pattern is a diagnostic clue, but diagnosis requires medical context and further evaluation.
Can a normal anion gap still indicate a medical problem?
Yes. A normal anion gap can still occur with illness, notably if the issue is a non-gap acid-base disorder, if albumin is low, or if the result is affected by laboratory error. Hyperchloremia, paraproteinemia, and other conditions can also complicate interpretation. If symptoms or other blood test results are concerning, a medical evaluation is still advisable.
Grasping identified and hidden anions turns the Anion Gap Calculator greater than a numerical tool. It becomes a hands-on way to read blood chemistry, detect a likely acid-base disorder, and connect lab results to the clinical significance of what is happening in https://anion-gap-range564.publishlane.com/posts/how-to-use-an-anion-gap-calculator-for-alkalemia-2 the body.