What Is the anion gap?
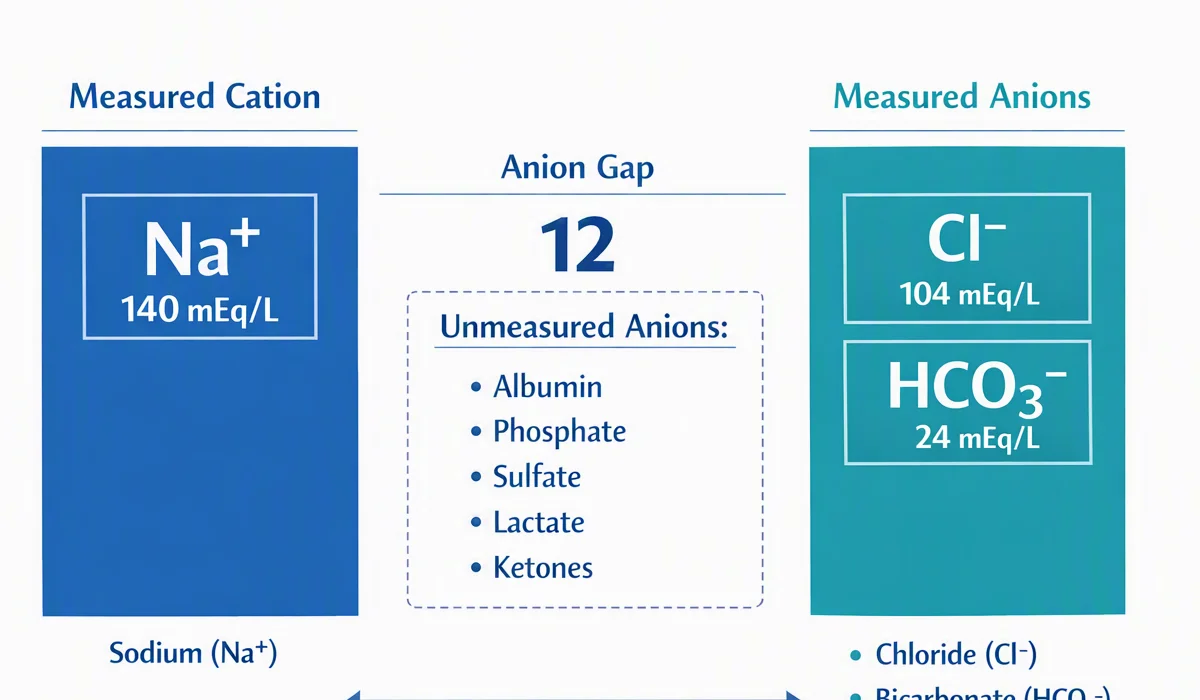
The anion gap is a calculated value that helps clinicians work through the distribution of charged particles in the blood. It is based on common electrolytes measured in a blood chemistry panel, especially sodium, chloride, and serum bicarbonate. In simple terms, the calculation shows the difference between the positively charged ions and the negatively charged ions that are routinely reported by the lab.
An Anion Gap Calculator is a useful way to perform this lab interpretation quickly. The result can help identify an elevated anion gap, which often points toward a metabolic problem involving extra acids in the bloodstream. A normal result does not always rule out disease, but it does guide the differential diagnosis and the next steps in evaluation.
The basic physiologic explanation is that the body maintains acid-base balance through a tightly controlled buffering system. When acid accumulates or bicarbonate falls, the anion gap can change. Potassium is sometimes included in certain formulas, but most clinical use focuses on sodium, chloride, and bicarbonate. Changes in albumin also matter because albumin is a major unmeasured negative charge in the blood.
Because the calculation reflects what is and is not measured directly, it is best understood as a hint rather than a diagnosis. It can reveal an electrolyte imbalance, suggest a hidden source of acidic metabolites, or indicate a broader metabolic derangement that needs closer review.
How Can Lactate Affect the Anion Gap?
Lactate stands as one of the key causes of a high anion gap because it is associated with lactic acid and lactic acidosis. As the body generates more lactate than it can remove, acid accumulates and uses up bicarbonate. That loss of bicarbonate contributes to metabolic acidosis, and the remaining negatively charged lactate helps increase the anion gap.
The reason is that lactate is not just a byproduct; it is part of a larger physiologic response to low oxygen delivery, impaired perfusion, or altered metabolism. In states of cellular hypoxia, tissues shift toward anaerobic metabolism, and lactate accumulation increases. The result can be a worsening gap along with worsening clinical signs of illness.
That said, the relationship is not perfectly linear. A patient may have substantially elevated lactate with only a modest change in the anion gap. For this reason, the clinical significance of lactate should be judged alongside symptoms, hemodynamics, and other lab values. The gap may be affected by other variables at the same time, including albumin, renal handling of acids, and overall metabolic state.
In clinical practice, lactate helps explain why a patient with an elevated anion gap may have worsening acidosis even before the source is obvious. Lactate is therefore both a diagnostic marker and a marker of severity assessment in many acute settings.
Why Is Lactic Acid Viewed as an Indirectly Measured Anion?
The anion gap is based on the idea of nonreported anions. The lab measures common ions such as sodium, chloride, and bicarbonate, but it does not directly report every charged substance in the blood. Lactate can accumulate as a negative ion and persist outside the standard routine calculation, which is why it is considered an unmeasured anion in this context.
When lactate rises, bicarbonate often falls because it cushions the excess acid. That shift modifies the measured portion of the chemistry panel while leaving the extra lactate “hidden” unless a serum lactate test is ordered. This is a key part of acid-base balance interpretation: the gap expands because the measured bicarbonate drops and the unmeasured acid load grows.
Albumin also plays a major role in this discussion. It is one of the largest normal unmeasured anions, and low albumin can mask an otherwise abnormal gap. In other words, a patient may have clinically important lactate-related acidosis without a dramatic gap if albumin is reduced. This is one reason the Anion Gap Calculator is most useful when interpreted in context rather than in isolation.
From a physiologic standpoint, the gap reflects the balance between measured cations and measured anions, plus all the unmeasured species that contribute to the body’s overall charge. Lactate is important because it represents a real alteration in chemistry, not just a number on a screen.
When Is Lactate Be Tested in a High Anion Gap?
Lactate testing should be obtained whenever high anion gap metabolic acidosis is present and the cause is not obvious. Providers frequently request it when the presentation suggests sepsis, shock, or tissue hypoxia. Such problems may swiftly compromise perfusion and oxygen delivery, leading to lactate buildup and worsening acidosis.
Important warning signs include hypotension, altered mental status, fever with signs of organ dysfunction, severe infection, and evidence of poor end-organ perfusion. Under these circumstances, lactate may detect ongoing stress before more dramatic laboratory abnormalities appear. It can also be valuable in critical illness, where metabolic changes evolve quickly and the source of acidosis may be multifactorial.
Even if the anion gap is only mildly elevated, lactate testing may still be appropriate if the patient looks ill. A normal or nearly normal gap does not rule out lactate-related pathology. That is especially true early in illness, when the body’s compensatory mechanisms and renal compensation may temporarily blunt the lab pattern.
In short, lactate should be checked when the clinical picture and the chemistry panel do not fully match, or when the risk of tissue-level oxygen debt is high. The number helps confirm whether the problem is a perfusion-related metabolic issue, a toxin, renal failure, or another cause of acidosis.
How to Analyze Lactate Alongside Anion Gap Results
The best interpretation comes from combining the arterial blood gas, serum lactate, base excess, and blood chemistry panel. Every measurement adds a separate layer of information. The chemistry panel shows the anion gap and bicarbonate level, the arterial blood gas defines pH and respiratory compensation, and the base excess helps quantify the metabolic component of the disorder.
If the anion gap is elevated and lactate is also high, the connection is direct: lactate is likely contributing to the acidosis. If the gap is high but lactate is normal, other causes of unmeasured acids should be considered. These may include renal failure, ketoacidosis, toxins, or less common metabolic conditions.
When lactate is high but the anion gap is not markedly abnormal, the result still matters. This can occur early in illness, with low albumin, mixed acid-base disorders, or simultaneous chloride changes that blunt the gap. It can also reflect a situation where lactate is elevated, but the total accumulation is not yet enough to cause a dramatic change in the measured electrolytes.
Lab interpretation should therefore follow a pattern rather than a single cutoff. Ask whether the patient has evidence of poor perfusion, hypoxia, infection, or organ dysfunction. Ask whether the anion gap is being influenced by albumin or other unmeasured anions. Then use the numbers to support the bedside picture rather than replace it.
A practical approach is this:

- Examine the anion gap and bicarbonate on the chemistry panel. Review the arterial blood gas for pH and compensation. Obtain serum lactate when the cause of acidosis is unclear or the patient is unstable. Determine whether renal failure, medication effects, or mixed disorders are changing the pattern.
This combined approach enhances the clinical significance of https://anion-gap-chart192.urbanvellum.com/posts/anion-gap-calculator-for-clinical-interpretation the result and helps distinguish true metabolic deterioration from a misleading isolated number.
Typical Reasons of High Lactate
A very common cause of high lactate is hypoperfusion. When blood flow is inadequate, cells are supplied with less oxygen and produce more lactate. This is why lactate serves as an important marker in shock states, significant dehydration, and impaired circulation. It indicates impaired oxygen delivery rather than just a lab abnormality.
Exercise can also raise lactate, typically in a brief and expected manner. In this setting, the increase is generally brief and improves as perfusion and oxygen delivery catch up with energy demand. The physiologic explanation is different from critical illness, but the lab finding may seem similar at first look.
Medications may also play a role. Some drugs disrupt mitochondrial metabolism, affect oxygen handling, or interact with liver function in a way that encourages lactate accumulation. A thorough medication review is part of the evaluation whenever lactate is unexpectedly high.

Liver dysfunction matters because the liver is a major site of lactate clearance. If the liver cannot clear lactate well, the level may continue to be high even if the original trigger improves. This can complicate severity assessment because the lab result may reflect both excess production and reduced clearance.
Renal failure is also relevant because impaired kidney function can lead to acid buildup and worsen metabolic acidosis. Although lactate is not primarily cleared by the kidneys, impaired acid handling by the kidneys and impaired compensation can worsen the overall metabolic state. The final result may be a more pronounced elevated anion gap or a mixed acid-base disorder that looks less classic than expected.
Additional causes of elevated lactate include serious infection, hypoxia, seizures, and toxin exposure. The key point is that lactate is not a diagnosis on its own. It is a marker that helps identify the origin of metabolic stress and how significant it may be.
Frequently Asked Questions on Lactate and Anion Gap Calculation
What is the role of lactate in anion gap calculation?
Lactate serves as an unmeasured anion that can increase the anion gap when it accumulates in the blood. Since it is not included in the routine chemistry panel, it may appear as part of a high anion gap metabolic acidosis. The Anion Gap Calculator can identify this pattern, but clinical interpretation still depends on the full picture, including serum bicarbonate, albumin, and the patient’s condition.
Does lactate necessarily increase the anion gap?
Not always. Lactate does not always cause a markedly increased anion gap. The gap can be influenced by albumin, other unmeasured anions, chloride shifts, renal compensation, and timing of the blood draw. A patient may have meaningful lactate accumulation with only a mild or even normal gap, especially early in illness or with a mixed acid-base disorder.
Can someone have high lactate with a normal anion gap?
Yes, it can. This can happen when the rise in lactate has not yet significantly changed the measured electrolytes, or when low albumin and other factors blunt the gap. It can also occur with mixed acid-base states that alter the expected pattern. That is why lactate should be interpreted with the arterial blood gas, blood chemistry panel, and clinical context rather than by the gap alone.
What is the method for measuring lactate in lab testing?
Lactate is measured with a serum lactate test, usually drawn from blood and analyzed by the laboratory. In many cases it is ordered alongside an arterial blood gas and a blood chemistry panel when metabolic acidosis is suspected. The result helps identify whether lactic acidosis is contributing to the acid-base disturbance and whether ongoing tissue hypoxia or hypoperfusion may be present.
When should a high anion gap prompt a lactate test?
A high anion gap should prompt a lactate test when the cause is not obvious, when the patient is unstable, or when there are signs of sepsis, shock, or tissue hypoxia. It is also appropriate when the differential diagnosis includes critical illness, renal failure, toxin exposure, or other metabolic disorder concerns. In these cases, lactate provides important clinical interpretation and helps guide the next steps in evaluation and treatment.