What exactly is the Anion Gap?
The anion gap is a measurement derived from a standard blood test that enables clinicians assess the balance of electrolytes in the body. It is based on a routine serum chemistry or electrolyte panel and is used to support assessment of acid-base balance. Although the term sounds highly specialized, the idea is straightforward: the result reflects the difference between measured positively charged ions and measured negatively charged ions in the blood.
This difference matters because it can indicate the presence of unmeasured anions or unmeasured cations that are not obvious from a basic panel alone. In clinical practice, the anion gap serves as a diagnostic tool and a quick way to guide result analysis when an acid-base disorder or other metabolic disturbance is suspected.
An anion gap calculator makes this process easier by using common lab values to calculate the result in seconds. But the number only becomes useful when you understand what it means in medical context. A normal result may be encouraging, while an abnormal one can point toward issues such as metabolic acidosis, low albumin, or other conditions that call for further review.
Anion Gap Calculation and Equation
The common anion gap equation uses measured values from the blood, specifically serum sodium, serum chloride, and serum bicarbonate. The most common anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some doctors use a different version that includes potassium, but most current tools use the more basic version above because it is broadly accepted and practical for routine interpretation.
Here is the simple logic behind the equation:
- Sodium represents the principal measured cation. Chloride and bicarbonate represent the primary measured anions. The gap reflects the gap between measured positive and negative charges.
When you calculate the anion gap, you are not finding a gap in the literal sense. You are approximating the amount of charge carried by unmeasured substances in the blood. That is why the anion gap equation is so useful for identifying an acid-base disorder and for recognizing patterns in a serum chemistry result.
A elevated result suggests excess unmeasured acids or other compounds, while a below-normal result can suggest a loss of negatively charged proteins or a measurement problem. Because of that, correct use of the anion gap formula depends on the entire lab picture, not just one isolated number.
How the Anion Gap Calculator Works
An anion gap calculator is built to streamline the math and limit manual errors. You provide the input values from the electrolyte panel, and the calculator handles the calculation steps automatically. In most cases, you supply sodium, chloride, and bicarbonate values, then the tool returns the anion gap along with a reference range or interpretation note.
The process usually is as follows:
- Enter the sodium value from the blood test. Provide the chloride value. Input the bicarbonate value. Examine the calculated result and assess it with the reference range.
Many users rely on an online calculator because it supports quick pattern recognition during result analysis. It is especially useful when reviewing an electrolyte panel in a busy clinical setting or when trying to understand whether a lab pattern suggests a broader metabolic issue.

Even though the calculator is simple, the numbers still need context. A value that falls within the reference range may still be abnormal if albumin is low or if another condition is changing the baseline. That is why the calculator is best viewed as a first step in interpretation, not the final answer.
In practical use, the calculator helps identify whether https://anion-gap-calculation.com/physiology/unmeasured-ions.html the result fits a typical normal anion gap pattern or whether further review is needed. It can also support decision-making when the goal is to understand possible causes of metabolic acidosis or other acid-base changes.
Normal Anion Gap Range and What Influences It
The normal range for the anion gap varies somewhat by laboratory because of changes in testing methods, analyzer calibration, and reporting practices. Here lab variation matters. A result that is deemed normal in one setting may be slightly different in another, so the lab’s own reference range should take priority.
Multiple factors can alter the number:

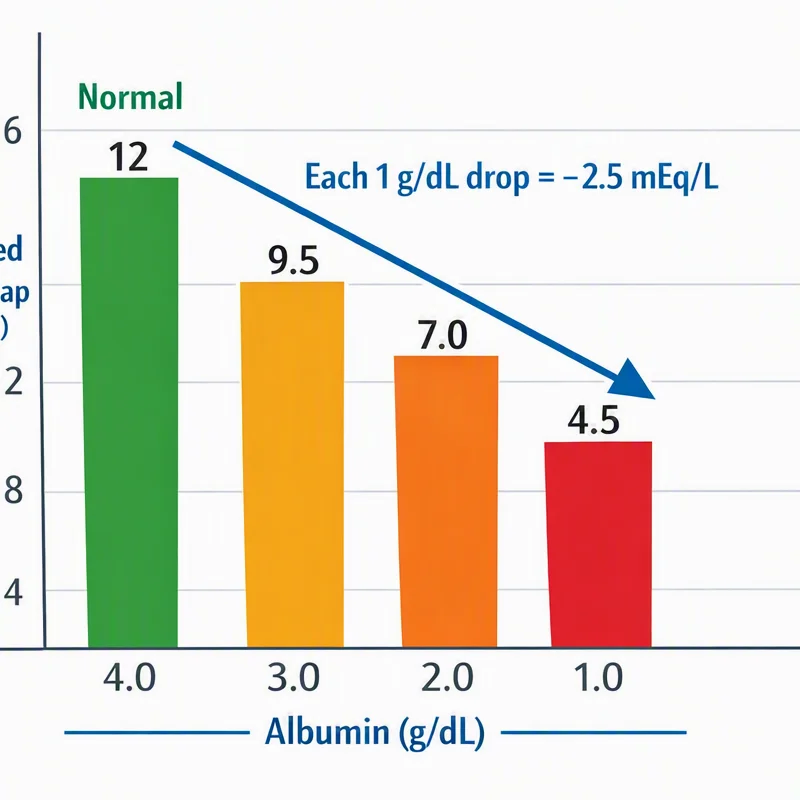
- Albumin: As albumin is a major unmeasured anion, lower levels can decrease the measured gap. Lactate: Elevated lactate can increase the gap because it adds unmeasured anions. Lab variation: Different instruments and methods may produce slightly different values.
Albumin is especially significant because it is one of the primary contributors to the anion gap. When albumin is low, the normal anion gap may appear misleadingly normal. In those cases, an albumin correction or albumin adjustment may be needed to estimate a more accurate corrected anion gap.
This matters because a patient can have a meaningful acid-base problem even if the raw number seems normal. Therefore, interpreting the value without checking albumin can lead to missed abnormalities. Similarly, elevated lactate can shift the result upward even before other abnormalities are obvious.
Raised Anion Gap: Frequent Causes
A elevated anion gap usually suggests the presence of unmeasured acids in the blood. The main clinical concern is acid-base disturbance, where acid accumulates or bicarbonate is used up in a way that increases the calculated gap.
These causes include:
- Lactate acidosis, often related to impaired tissue oxygen delivery, severe illness, or decreased lactate clearance. Ketoacidosis, which can occur when ketone bodies build up during insulin deficiency, starvation, or other metabolic stress. Kidney failure, where reduced acid excretion causes acids to build up. Toxic ingestion, including certain substances that generate unmeasured acids or interfere with normal metabolism.
These causes are important because they indicate different treatment pathways. For example, lactic acid buildup points to a search for tissue hypoperfusion or severe infection, while ketone-related acidosis points toward abnormal fat metabolism and requires a different management approach. Kidney failure may cause acid retention over time, and poisoning can produce a dangerous metabolic picture that needs urgent assessment.
A high value is not a diagnosis by itself. It is a clue that should be read alongside symptoms, history, and the rest of the blood test results. In many cases, it prompts more testing to identify the underlying cause and to determine how severe the metabolic disturbance is.
Low Anion Gap: Typical Causes
A decreased anion gap is not as common than a high one, but it can still be important clinically. One of the most common explanations is hypoalbuminemia, because albumin is a negatively charged protein that contributes to the normal gap. When albumin falls, the calculated value can fall with it.
Other common causes include:
- Paraproteinemia, where abnormal proteins in the blood alter the balance of measured and unmeasured ions. Lab error, including specimen issues or measurement problems that distort the reported electrolytes.
Hypoalbuminemia is especially relevant because it can obscure a serious condition if the result is interpreted without an albumin correction. In some patients, the corrected value may reveal a more significant disorder than the unadjusted number suggests. This is why a corrected anion gap can be more revealing than the raw calculation alone.
Paraproteinemia should be considered when abnormal proteins are present, particularly if other findings do not match the apparent result. And because lab error is always possible, an unexpected low result should be reviewed carefully before drawing conclusions. Repeating the test or checking the full electrolyte panel may help confirm whether the number is real.
Clinical Use of the Anion Gap in Acid-Base Disorders
The anion gap is particularly helpful when used as part of a more comprehensive assessment of acid-base disorders. It helps differentiate different types of metabolic acidosis and strengthens the work of pattern recognition when reviewing a blood test, electrolyte panel, and serum chemistry results together.
In practice, the anion gap helps clarify questions such as:
- Could the acidosis be the acidosis related to accumulation of unmeasured acids? Does the pattern suggest bicarbonate loss instead? Is the gap elevated enough to prompt looking for lactate, ketones, toxins, or renal dysfunction?
Another important concept is the delta gap, which compares the change in anion gap with the change in bicarbonate. This can help identify mixed disorders, where more than one metabolic process is happening at the same time. That is useful because a patient may have a high anion gap acidosis and another acid-base problem at once.
A blood gas is often interpreted alongside the anion gap to offer a fuller picture of acid-base status. The blood gas shows pH and respiratory compensation, while the anion gap helps reveal the underlying metabolic component. Together, they improve clinical significance and help with cause assessment.
This is why the anion gap remains a practical diagnostic tool: it turns a simple lab calculation into a helpful guide for evaluating complex metabolic disturbances.
Ways to Interpret Findings Carefully
Sound clinical interpretation needs more than reviewing one number. The anion gap should be reviewed in the setting of clinical symptoms, the entire electrolyte panel, medication history, kidney function, and any other signs of illness. A result that seems abnormal may be explained by timing, fluid status, protein changes, or measurement differences.
Safe interpretation involves multiple steps:
- Check the values used in the calculation. See whether the lab’s reference range changes from other sources. Assess albumin and consider albumin adjustment if needed. Look for signs of electrolyte imbalance or metabolic acidosis. Look for clinical clues that support or reduce a suspected cause.
If the result suggests a major abnormality, a medical evaluation is necessary. This is especially true when symptoms such as confusion, rapid breathing, dehydration, vomiting, or severe weakness are present. The anion gap is useful, but it does not replace a full assessment of the person and the illness.
In practical terms, the number should inform the next step, not serve as the final conclusion. Pairing the calculator result with clinical context improves accuracy and reduces the risk of missing an important problem.
Common Questions
Why use the anion gap calculator?
The anion gap calculator is used to calculate the anion gap from common blood test values, usually sodium, chloride, and bicarbonate. It helps with interpretation of acid-base balance and can point toward a metabolic disturbance such as metabolic acidosis.
What formula is used for the anion gap?
The most common anion gap equation is: sodium minus the sum of chloride and bicarbonate. In short, the anion gap formula is sodium − (chloride + bicarbonate). Some versions may include potassium, but the simpler formula is widely used.
What is a normal anion gap result?
The expected range varies by the testing facility and analysis used, so the listed range on the lab report should be checked first. A result in the expected range generally implies no major increase of hidden acids, but albumin and lab variation can affect the value.
What leads to a high anion gap?
A elevated anion gap is often caused by acid buildup from problems including lactic acidosis, ketone buildup, impaired kidney function, or poisoning. These conditions contribute unmeasured acids to the blood and increase the calculated value.
Can a low anion gap signal a medical problem?
It can. A low anion gap can be associated with hypoalbuminemia, protein abnormalities, or measurement error. It may also indicate other changes in electrolytes or proteins, so it should be reviewed in the full clinical picture rather than overlooked.